Introduction
Medicaid is a program funded jointly by the state and federal governments. Its core functions include paying medical providers for health care services rendered to society’s most vulnerable: the disabled, the blind, the elderly, disadvantaged children, and low-income parents.
After resisting for more than a decade, however, North Carolina expanded its Medicaid program in 2023. North Carolina’s Medicaid expansion extended coverage to childless, able-bodied adults aged 19 to 64 with incomes up to 138 percent of the federal poverty level. Initial state projections anticipated that enrollment would peak at approximately 600,000 individuals. However, as of September 2025, enrollment has exceeded expectations, reaching 680,000 participants.
This surge in enrollment has strained the Medicaid program’s capacity. The rapid addition of nearly 700,000 new enrollees has led to a reallocation of resources that, in practice, disadvantages traditional Medicaid populations, such as individuals with disabilities, the elderly, and disadvantaged children.
As funds and provider availability are increasingly directed toward expansion enrollees, these traditional groups experience longer wait times and reduced provider access. According to fiscal year (FY) 2023–24 data from the Centers for Medicare and Medicaid Services, North Carolina has the slowest emergency rooms in the Southeast and the seventh-slowest in the nation, with a median visit time of 3 hours and 15 minutes.
The resulting crowding out raises concerns about whether the Medicaid system can effectively serve newly eligible able-bodied adults and those with longstanding, greater medical needs. Post expansion, total Medicaid expenditures in North Carolina have skyrocketed from $21.5 billion in FY 2022–23 to $27.8 billion in FY 2023–24, a staggering 29 percent increase. Of the FY 2023–24 expenditures, $18.9 billion, or 68 percent, was provided by the fiscally unstable federal government, which is more than $37 trillion in debt.
Federal dollars cover 90 percent of the costs of the expansion population, while the state share is covered by a provider tax levied on the state’s health care providers. As part of the 2021 American Rescue Plan Act, North Carolina received a $1.8 billion “signing bonus” from the federal government in exchange for the expansion, funds that were paid out over two years.
While advocates, such as former Gov. Roy Cooper, emphasized how the expansion would not cost state taxpayers any money, the 2025 passage of the federal One Big Beautiful Bill Act (OBBBA) threatens to upend this claim. Thankfully, the 2023 legislation that authorized Medicaid expansion included a safeguard: If the approved revenue sources cannot fully fund the nonfederal share of the cost, the state will discontinue expansion coverage.
The OBBBA lowers the maximum provider tax rate the state can charge, which will reduce the provider tax revenue available to fund the state’s share of the cost. When revenue from this source falls low enough that it no longer covers the state’s 10 percent share of the cost, the 2023 safeguard will kick in. North Carolina legislators will be left with a difficult political decision: break their promise and raise other taxes, reduce eligibility and coverage, or terminate Medicaid expansion.
Key Facts
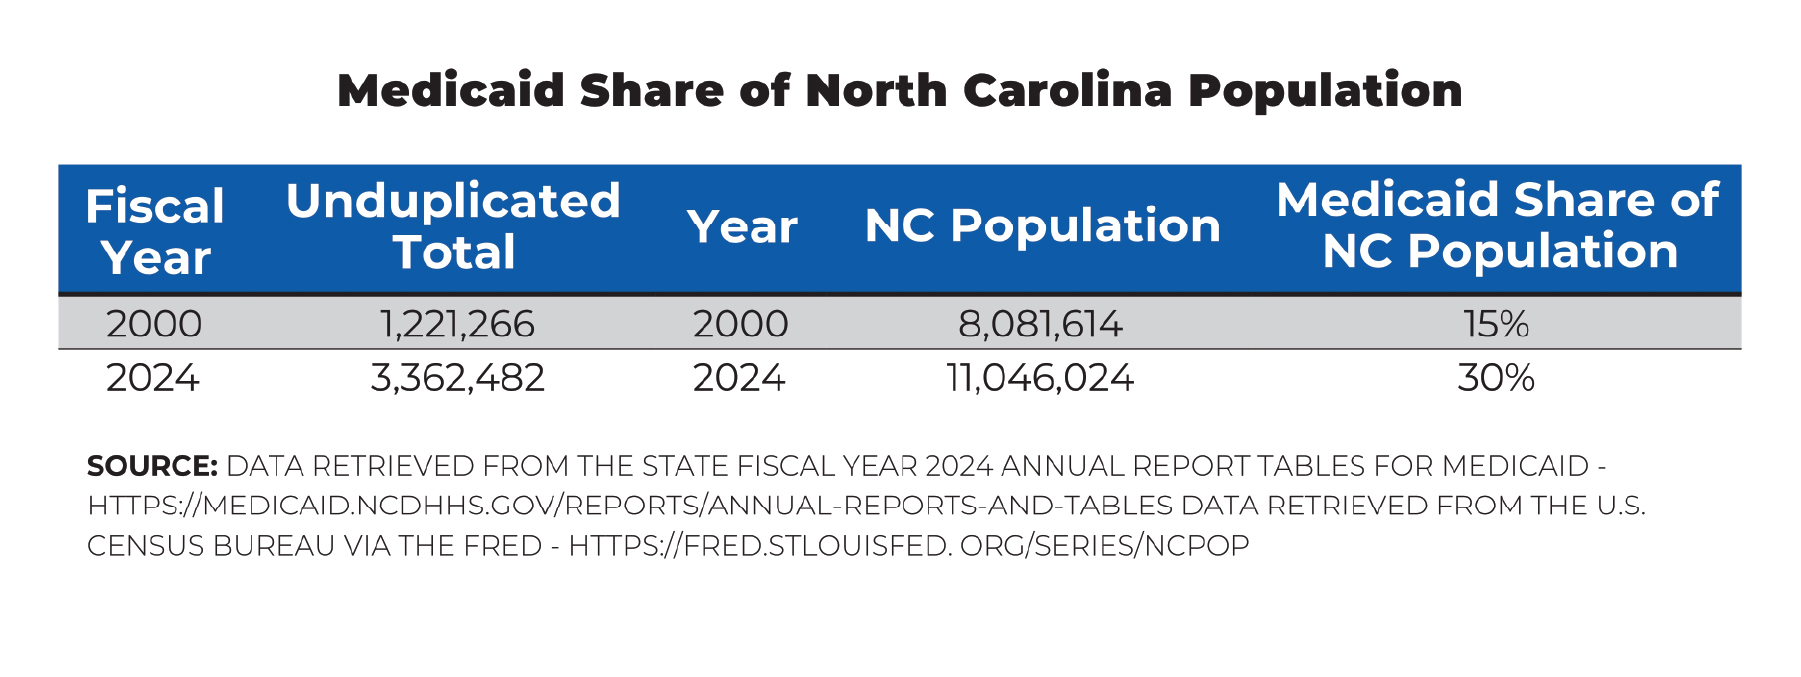
- Since 2000, the share of North Carolinians on Medicaid has increased from approximately 15 percent to a concerning 30 percent, effectively crowding out the vulnerable groups that Medicaid was traditionally designed to protect. In fact, the number of disabled, blind, and elderly Medicaid enrollees increased by 38 percent from FY 1999–2000 to FY 2023–24, yet their share of the total Medicaid recipients in North Carolina decreased from 30 percent to 15 percent during the same period. This trend has been exacerbated by North Carolina’s recent Medicaid expansion, which added hundreds of thousands of able-bodied adults to the program, further diluting the focus and resources intended for the most vulnerable populations.
- From FY 2018–19 to FY 2023–24, the median emergency room visit time in North Carolina increased from 2 hours and 36 minutes to 3 hours and 15 minutes, a 25 percent jump that downgraded the state’s wait times from eleventh longest to seventh longest. North Carolina’s Medicaid expansion, which took effect in December 2023, exacerbated this trend by adding hundreds of thousands of new enrollees and causing already strained emergency rooms to experience greater crowding and longer wait times.
- Given the current trajectory, Medicaid expenditures are not sustainable for the state and federal governments. From FY 2009–10 to
- FY 2023–24, total Medicaid expenditures in the state increased from $12.8 billion to $27.8 billion, a staggering 116 percent leap. More than 40 percent of that growth occurred from FY 2022–23 to FY 2023–24 alone. This surge was even more pronounced at the state level: Over those 14 years, state appropriations for Medicaid increased from $2.3 billion to $5.5 billion (136 percent). In recent years, the upward trend has accelerated: the FY 2025–26 Senate and House budget proposals would allocate $6.4 billion in net General Fund state appropriations to Medicaid, an increase of 60 percent since $4 billion was allotted just four years prior in FY 2021–22 (no budget for FY 2025-26 has been approved as of this writing).
- North Carolina imposes taxes on health care providers to cover its share of Medicaid expansion costs. From 2028 to 2032, the OBBBA will incrementally reduce the cap on these “provider taxes” from 6 percent to 3.5 percent, a change that could dismantle North Carolina’s Medicaid expansion financing model, which depends on these taxes to fund the state’s 10 percent share. The OBBBA also implements a requirement that Medicaid recipients must work or volunteer at least 80 hours per month to maintain eligibility starting in The North Carolina Department of Health and Human Services estimates that the work requirement could result in as many as 213,000 Medicaid expansion enrollees losing coverage.
Recommendations
1. North Carolina should repeal Medicaid expansion.
As soon as the federal enactment of the OBBBA or any other rule triggers the conditions set out in the 2023 safeguard, policymakers should introduce a bill to end coverage for the Medicaid expansion population. Attempting to continue the expansion program would be fiscally irresponsible and risk continued coverage for the traditional Medicaid population.
2. North Carolina must prioritize the most vulnerable.
Lawmakers must ensure that traditional Medicaid populations, like the elderly and disabled, remain a top priority and are not displaced by the expansion of coverage to able-bodied adults. Due to their complex and long-term needs, these groups already represent a significant yet justified commitment of state resources.
3. North Carolina should advance market-based alternatives to Medicaid expansion.
Medicaid expansion extended coverage to able-bodied, childless adults, many of whom are not working full time — often by choice. This encourages dependency on public programs at a time when many employers offer entry-level jobs with health benefits. Moreover, before Medicaid expansion, many North Carolinians accessed care through a network of community clinics, direct-pay providers, and charitable organizations. Policymakers should build on these foundations by expanding access to market-based solutions that encourage competition, lower costs, and empower individuals to choose care that fits their needs.